The first week brought nausea and loose stools, mainly after breakfast. Taking it with a proper meal helped, and the symptoms became less distracting after the regimen was adjusted. I kept a note of my readings and the times I felt unwell, which made the review more useful.
Metformin lowers blood glucose by reducing glucose production in the liver and helping the body respond better to insulin. Metformin is used mainly by adults with type 2 diabetes alongside eating-pattern changes and physical activity.
Formulation
Metformin Hydrochloride Composition
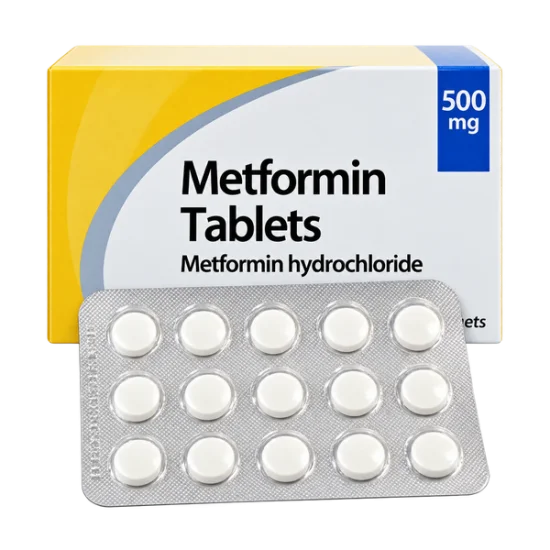
Each tablet supplied as this product contains metformin hydrochloride. Metformin hydrochloride belongs to the biguanide class of glucose-lowering medicines.
The drug does not replace insulin. Its main action is to reduce unnecessary glucose production and improve the body’s response to its own insulin. Medsafe product information describes metformin as a treatment used with diet and exercise for type 2 diabetes [1]. The regimen for the chosen strength should be confirmed with a healthcare professional before starting.
Therapeutic indications
Metformin is an oral glucose-lowering treatment for type 2 diabetes. It reduces excess glucose released by the liver. It also improves insulin sensitivity. These effects help the body use circulating glucose more efficiently. Treatment still requires food planning, physical activity, blood-glucose monitoring and regular clinical review.
Insulin is a hormone that helps glucose move from the bloodstream into body tissues. In type 2 diabetes, the liver may release too much glucose and the body may respond poorly to insulin. This reduced response is called insulin resistance.
Dosage and administration
The regimen for the selected strength should be confirmed with a healthcare professional before starting. Metformin is taken by mouth, with the timing and frequency set according to the prescribed formulation and the person’s glucose results, tolerance and kidney function.
- Take each dose at the prescribed time, usually with food when directed.
- Swallow tablets with water.
- Do not increase, reduce or stop the treatment without a planned review.
- If a dose is missed, follow the missed-dose instruction provided with the dispensing information rather than doubling the next dose.
- Tell the prescriber about persistent vomiting, diarrhoea, dehydration, severe infection or a planned procedure.
- Expect kidney-function review during ongoing treatment.
Clinicians may begin with a lower regimen and adjust it gradually. This approach can reduce gastrointestinal effects while the body adapts. Metformin is cleared through the kidneys, so renal blood tests influence whether the treatment remains suitable and how it is adjusted.
During severe dehydration or acute illness, temporary interruption may be required under clinician direction. Contrast imaging and surgery can also require a planned review because kidney function may change around these events.
When this is not for you
NOT for you if: a clinician has advised that severe kidney impairment or another medical condition makes metformin unsuitable.
Possible side effects
The most familiar adverse effects are gastrointestinal. Nausea, diarrhoea, abdominal discomfort, reduced appetite and a metallic taste may occur after treatment begins or after the regimen is increased. Gradual adjustment and taking doses with food can improve tolerance for some patients.
| Symptom | Usual practical response |
|---|---|
| Nausea or abdominal discomfort | Take the dose with food as directed and report persistent symptoms for a regimen or formulation review. |
| Diarrhoea | Maintain appropriate fluid intake and seek advice if symptoms are severe, prolonged or associated with dehydration. |
| Metallic taste | This can occur with metformin and is often unpleasant rather than dangerous by itself; report persistent or severe changes. |
Gastrointestinal Effects
Diarrhoea that continues for days should not be silently tolerated for weeks. Fluid loss can cause dehydration, and dehydration can place additional stress on kidney function. Severe vomiting or diarrhoea may require temporary treatment instructions from a clinician.
Some people experience symptoms after every dose, while others notice them mainly after a dose increase. A clinician may review the timing, gradual adjustment plan or suitability of an extended-release formulation.
Metallic Taste Changes
A metallic taste is a recognised metformin effect. It may affect appetite or make certain foods less enjoyable. It is usually discussed during a treatment review if it persists, becomes severe or occurs with other symptoms.
Lactic acidosis is a rare but serious condition in which lactic acid accumulates in the bloodstream and the body becomes too acidic. Metformin-associated lactic acidosis is more likely when metformin accumulates because kidney function is severely impaired or when the body has major problems with oxygen delivery.
The risk is also relevant during severe dehydration, serious infection, significant liver problems, heavy alcohol exposure or other acute conditions that affect oxygen use and metabolism. The European Medicines Agency describes kidney function as a central consideration in metformin safety [2].
Lactic Acidosis Risk Factors
Urgent medical assessment is needed for unusual and worsening weakness, difficulty breathing, persistent vomiting, marked abdominal discomfort, confusion, unusual sleepiness or feeling severely unwell. These symptoms do not prove lactic acidosis, but they should not be ignored in someone taking metformin.
Do not attempt to diagnose this complication from ordinary muscle soreness, a brief stomach upset or a single abnormal glucose reading. The response depends on the full clinical picture and blood tests.
Kidney Function Monitoring
Metformin is cleared through kidney function. Regular renal assessment helps determine whether treatment remains appropriate. The review becomes more urgent after severe dehydration, a major illness, a procedure or imaging involving contrast.
Long-term metformin use can lower vitamin B12 levels in some people. The risk is more relevant when treatment continues for a long period, the regimen is higher, or other factors already reduce B12 absorption.
Possible signs include fatigue, anaemia, a sore or inflamed tongue, numbness, tingling, balance problems or unusual weakness. These symptoms have many possible causes, so testing is more useful than starting supplements solely because metformin is being used.
Vitamin B12 Deficiency Symptoms
Numbness and tingling deserve attention because untreated vitamin B12 deficiency can affect nerves. A person should not assume that every symptom is caused by diabetes or metformin. Blood testing can help separate B12 deficiency from nerve complications of diabetes, anaemia and other conditions.
Long-Term Monitoring Plan
The monitoring interval is individualised according to treatment duration, symptoms, diet, medical history and clinical risk. A clinician may arrange a blood test and decide whether dietary measures, supplementation or further investigation is appropriate.
The World Health Organization recognises vitamin B12 deficiency as a cause of anaemia and neurological problems, which is why persistent neurological symptoms require assessment rather than self-treatment [3].

How it affects the body
Metformin acts mainly on the liver, where it reduces gluconeogenesis, the process of making new glucose. It also improves insulin sensitivity in peripheral tissues. These effects can reduce blood-glucose levels without directly stimulating the pancreas to release more insulin.
Metformin alone generally has a lower risk of hypoglycaemia than insulin or sulfonylureas. The risk changes when it is combined with those medicines.
Common mistakes
Metformin problems often arise from routine errors rather than from a single unusual reaction.
- Doubling a missed dose: This can increase gastrointestinal effects. Use the specific missed-dose instruction supplied for the prescribed formulation.
- Stopping suddenly without a plan: Blood glucose may rise when treatment is stopped. A clinician should decide whether treatment needs replacement or adjustment.
- Crushing an extended-release tablet: Crushing can disrupt the slow-release design of products such as Glucophage XR.
- Ignoring persistent diarrhoea: Ongoing fluid loss can cause dehydration and affect kidney safety.
- Taking doses on an empty stomach despite meal instructions: This can make nausea or abdominal discomfort more troublesome.
- Failing to mention metformin before a procedure: Imaging, surgery or acute illness may require temporary treatment changes.
- Assuming metformin prevents all glucose problems: Blood glucose can still rise during infection, stress, missed meals, reduced activity or progression of diabetes.
The renal safety issue is easy to underestimate. A person who has tolerated metformin for years can still need a review during severe vomiting, diarrhoea or dehydration.
Missed-Dose and Discontinuation Errors
The correct response to a missed dose depends on the formulation and the timing of the next scheduled dose. Do not create a personal catch-up schedule. Use the dispensing instructions and seek prompt clarification from the prescribing or dispensing team when the written instructions are unclear.
Extended-Release Tablet Handling
Glucophage XR releases metformin gradually. The tablet should generally be swallowed whole, subject to the local product information for that formulation. A tablet that appears partly intact after passage through the digestive tract does not necessarily indicate treatment failure.
Comparison
Metformin may be prescribed alongside insulin or sulfonylureas when one treatment does not provide adequate glucose control. Combination treatment can improve glucose management, but it also requires a clear monitoring plan.
| Medicine class | Main role and monitoring issue |
|---|---|
| Metformin | Reduces liver glucose production and improves insulin sensitivity; gastrointestinal tolerance and kidney function require review. |
| Insulin | Replaces or supplements insulin activity; low blood glucose can occur if the dose, food intake or activity pattern changes. |
| Sulfonylureas | Stimulate insulin release from the pancreas; hypoglycaemia is a key combination-treatment concern. |
Metformin alone does not usually cause hypoglycaemia to the same extent as insulin or a sulfonylurea. When medicines are combined, new sweating, shaking, confusion, sudden weakness or intense hunger should prompt a blood-glucose check and action according to the diabetes care plan.
Do not independently change insulin or sulfonylurea doses.
Combination treatment needs coordinated adjustment.
What doctors say
In clinical practice, doctors often judge metformin by three questions: is glucose improving, is the person tolerating the regimen, and does kidney function remain suitable? A single glucose result rarely answers all three.
Physicians also look beyond the medicine. Eating patterns, activity, illness, sleep, other diabetes treatments and missed doses can all influence glucose readings. A rising result does not always mean that metformin has stopped working, while a normal reading does not prove that every part of diabetes management is stable.
One practical observation is that tolerability often determines consistency. A person who is afraid of another episode of diarrhoea may skip doses, even when the treatment could still be useful after a supervised adjustment.
Comparison
Common questions
Which symptoms mean stopping and seeking urgent medical help?
Urgent symptoms include severe or worsening weakness, difficulty breathing, persistent vomiting, marked abdominal discomfort, confusion or unusual sleepiness. These symptoms can have several causes, but Medsafe safety information current for 2025 identifies serious illness and kidney-related problems as situations requiring prompt assessment. Do not take an additional dose while waiting for urgent medical instructions if a clinician tells you to stop.
Can I drive, concentrate or work with machinery while taking Metformin?
Metformin by itself does not usually impair concentration or coordination, according to standard medicine information reviewed by Medsafe in 2025. Driving risk can change if blood glucose becomes too low because metformin is combined with insulin or a sulfonylurea. Sweating, shaking, confusion, blurred vision or sudden weakness require a blood-glucose check and action under the diabetes care plan before driving or operating machinery.
How soon does the effect become noticeable?
Metformin begins affecting glucose production after treatment starts, but the measurable result develops through regular dosing and clinical review. The NHS and WHO diabetes information available in 2025 describe glucose management as a continuing process rather than an immediate symptom-relief effect. Do not increase the regimen because a reading has not changed after one or two doses; use the monitoring plan agreed with the diabetes team.
Can Metformin be used during pregnancy and breastfeeding?
Pregnancy and breastfeeding decisions should be individualised with the prescriber, as stated in European Medicines Agency product information reviewed in 2025. Diabetes itself requires careful management during pregnancy, and treatment may need adjustment as glucose needs change. A person who is pregnant, planning pregnancy or breastfeeding should provide that information before the regimen is started or changed.
What should I do if the expected result does not occur?
A lack of improvement should prompt a structured review rather than self-directed dose escalation. Medsafe guidance current for 2025 supports reviewing adherence, food intake, activity, illness, kidney function, other medicines and the diagnosis before changing treatment. Bring a record of glucose readings, missed doses and symptoms so the prescriber can decide whether Metformin remains suitable alone or needs a planned combination treatment.
Do you offer anonymous delivery?
Your order will be securely packed and shipped within 24 hours. This is exactly what your package will look like (images of an actual item sent). It has the size and look of a regular private letter (24x11x0.7 cm) and its contents cannot be seen.
Metformin Clinical Advantages and Limitations
Metformin has an established role in type 2 diabetes because it lowers glucose through a mechanism that does not depend on forcing the pancreas to release insulin. It is available in immediate-release and extended-release formulations, allowing clinicians to consider administration patterns and gastrointestinal tolerance.
Its limitations are equally practical:
- Digestive effects can interfere with adherence.
- Kidney function restricts suitability for some people.
- Dehydration and acute illness can change renal safety.
- Long-term use can lower vitamin B12 in some patients.
- It is not suitable for every person with diabetes.
- It does not replace physical activity, food planning or clinical monitoring.
A physician’s treatment choice is shaped by glucose targets, kidney function, other medicines, symptoms, treatment history and the person’s wider diabetes plan. The formulation is not selected by convenience alone.
Sources
- Medsafe (2025). Metformin hydrochloride 500 mg tablets: Data Sheet and Consumer Medicine Information.
- European Medicines Agency (2024). Summary of Product Characteristics (SmPC) — metformin-containing medicines.
- World Health Organization (2024). Vitamin B12 deficiency: fact sheet and health information.
Reviews: Metformin
I had taken metformin for several years before a bout of diarrhoea left me dehydrated. I nearly carried on as normal, but the medical team reviewed my kidney function and gave me temporary instructions. The main lesson was not to treat persistent stomach symptoms as something I simply had to tolerate.
My glucose readings improved gradually rather than overnight. I disliked the metallic taste at first, and I missed a dose once before taking two together later that day. The pharmacist explained why doubling was a poor idea, so I now follow the written missed-dose instructions.